

One of the most common injuries I treat are hip fractures. I see what they do to patients, and I see what they cost. A 74 year old woman falls in her bathroom, fractures her proximal femur, and within hours (ideally) she is in an operating room. The surgery goes well. The implant is stable. But the downstream consequences unfold over months and years: skilled nursing stays, readmissions, deconditioning, loss of independence. Her eight year mortality risk just increased by 83%. Medicare will spend more than $50,000 on this single event. A set of grab bars and better lighting in that bathroom might have cost $500.
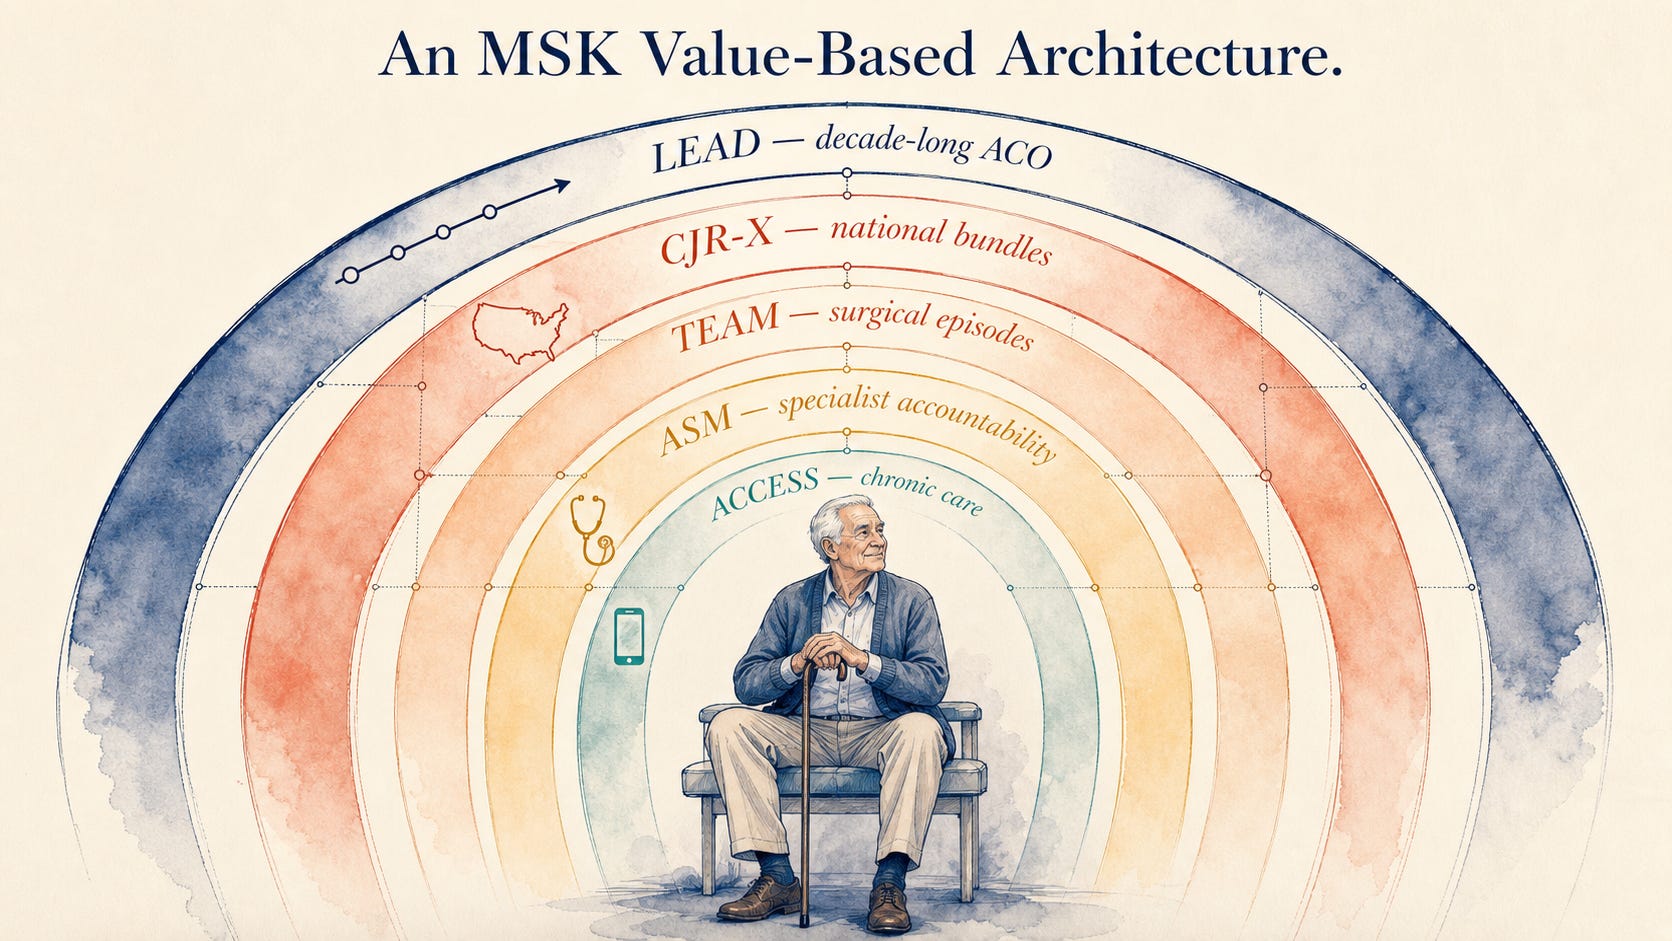
This is the arithmetic that should be driving musculoskeletal care policy in the United States. It largely isn’t, but CMS appears to be building toward it through a series of models that, read together, amount to a coherent architecture for musculoskeletal (MSK) value based care. That’s what this piece is about.
The Scale of the Problem
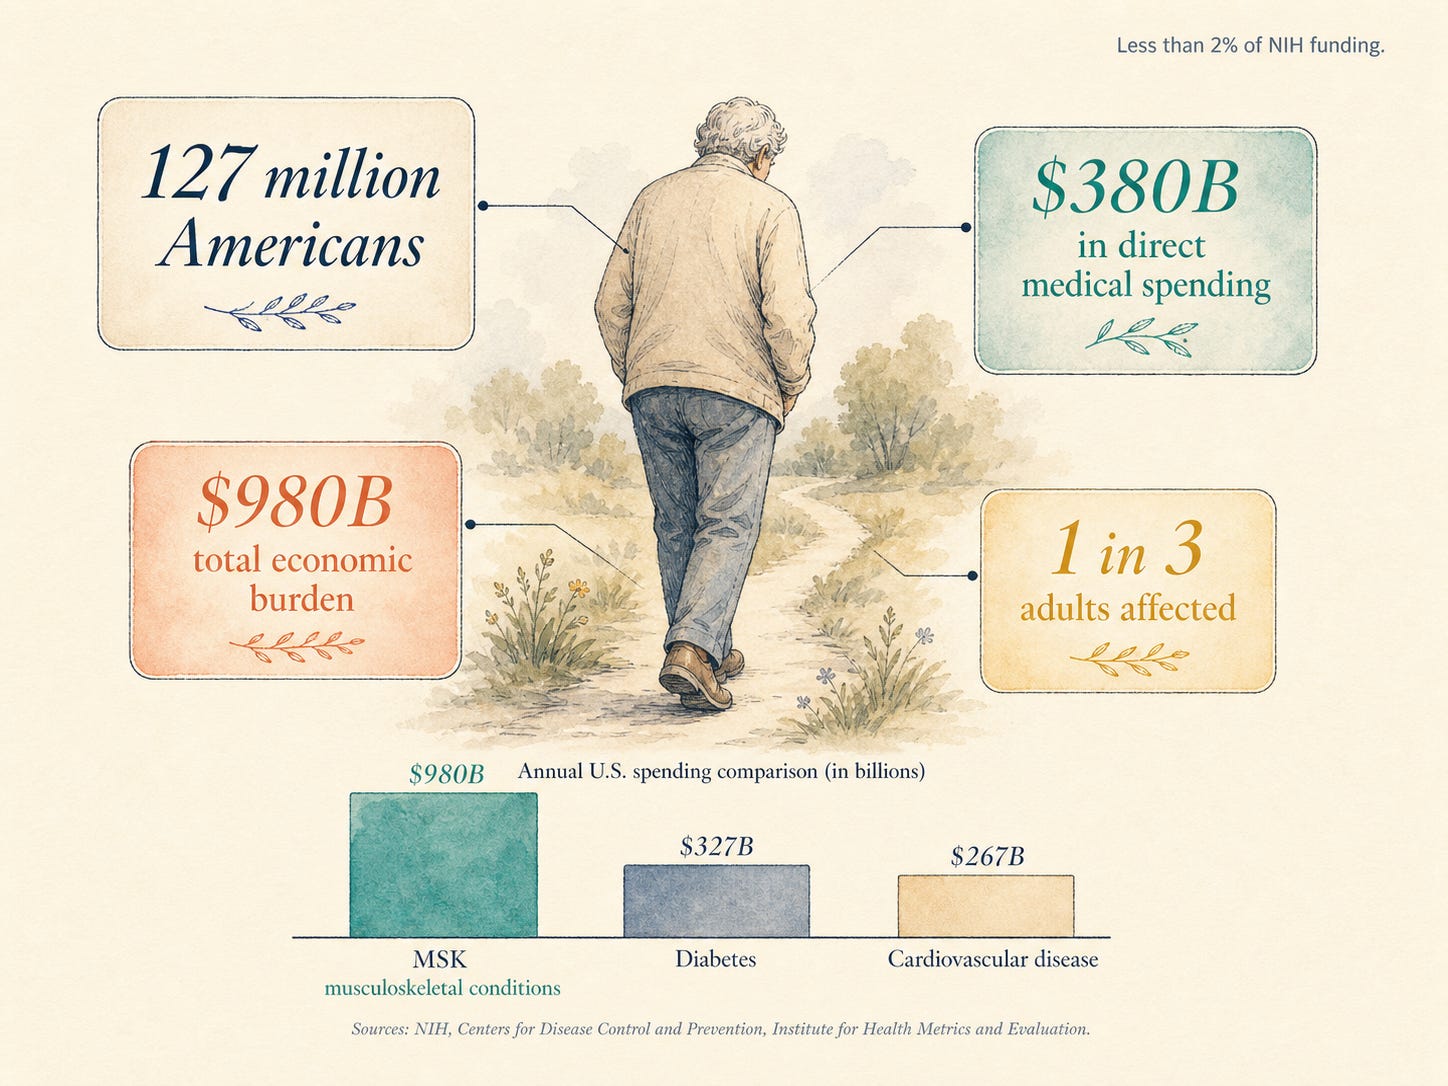
Musculoskeletal conditions are the leading cause of disability and the highest category of healthcare spending in the United States. More than 127 million Americans are affected by disabling musculoskeletal conditions, roughly one in three adults. Direct medical spending exceeds $380 billion annually, surpassing diabetes and cardiovascular disease. Including indirect costs like lost productivity and disability, the total economic burden approaches $980 billion per year.¹˒²˒³
Low back pain alone accounts for more years lived with disability than any other condition globally, and its intersection with the opioid crisis has compounded the public health burden: opioid use among patients with back problems increased 423% between 1997 and 2005. The economic burden of chronic pain and opioid use disorders in the U.S. exceeds $500 billion annually.⁴˒⁵
Falls occupy a particularly critical position in this landscape. More than 14 million older adults report falling each year, generating approximately 3.85 million emergency department visits at a total cost of roughly $80 billion per year, projected to exceed $101 billion by 2030.⁶˒⁷ More than 53 million Americans either have osteoporosis or are at elevated risk due to low bone mass.⁸ Among Medicare beneficiaries, hip fracture patients account for nearly $6 billion in annual spending, and a hip fracture increases the likelihood of subsequent hospitalization by 231%.⁸˒⁹
Despite this burden, musculoskeletal research receives less than 2% of NIH research funding, making it among the most underfunded disease categories relative to its disability burden.¹⁰
The Reimbursement Paradox: Declining Payment for High Value Care
Against this backdrop, something troubling has been happening to orthopedic reimbursement for decades. CMS appears to view orthopedic surgery, and total joint replacement in particular, as a cost center to be managed down rather than a high value intervention to be optimized.
Between 2000 and 2024, mean Medicare reimbursement for primary total hip and knee arthroplasty decreased by 56%. Revision arthroplasty reimbursement declined by 51% over the same period.¹¹ These declines are not proportional to what other specialties have experienced: reimbursement reductions for primary TKA and THA have been disproportionately greater than the mean decline for other high volume inpatient procedures, by orders of magnitude.¹² Mathematical modeling forecasts that total reimbursement for primary TJA could decrease by 85% to 86% by 2030, with surgeons earning less than $15 per hour per procedure in 2023 dollars.¹³
The 2026 Medicare Physician Fee Schedule added a 2.5% efficiency adjustment (effectively a cut) for surgical procedures, reflecting CMS’s position that technology has made procedures more efficient, even as operative complexity and patient acuity continue to increase.¹⁴
This decline is happening while demand is surging. Primary total knee arthroplasty volume grew from 603,704 in 2013 to over 1 million in 2022, and is projected to reach nearly 2.8 million by 2040.¹⁵˒¹⁶ The American Joint Replacement Registry has captured over 4 million procedures and growing.¹⁷
I don’t agree with the commoditization of orthopedic procedures. Total joint arthroplasty is among the most cost effective interventions in all of medicine, with consistent evidence of significant quality adjusted life year gains across populations.¹⁸ It provides tremendous value for millions of people around the world each year. Treating it as a line item to be squeezed undermines the workforce and infrastructure that delivers it.

But I do think there is a strong case for improving and enhancing episode of care management, both pre and postoperatively, as well as for chronic MSK pain, which contributes to significant disability and morbidity annually. The question isn’t whether orthopedic care is valuable. It is. The question is whether we can build systems around that care that reduce avoidable costs, improve outcomes, and demonstrate value in formats that payers recognize.
That’s what CMS appears to be doing, through multiple channels simultaneously.
The Models: CMS Signals a Different Approach
CMS is signaling that musculoskeletal care needs a fundamentally different approach, and the evidence extends well beyond any single model. The mandatory bundled payments, chronic care tracks, population health programs, specialist accountability measures, and structured falls prevention episodes CMS has launched over the past two years all converge on MSK care. Reading them separately misses the coherence.
It helps to walk through each model individually before considering how they interact.
TEAM: The First Wave of Mandatory Episode Accountability
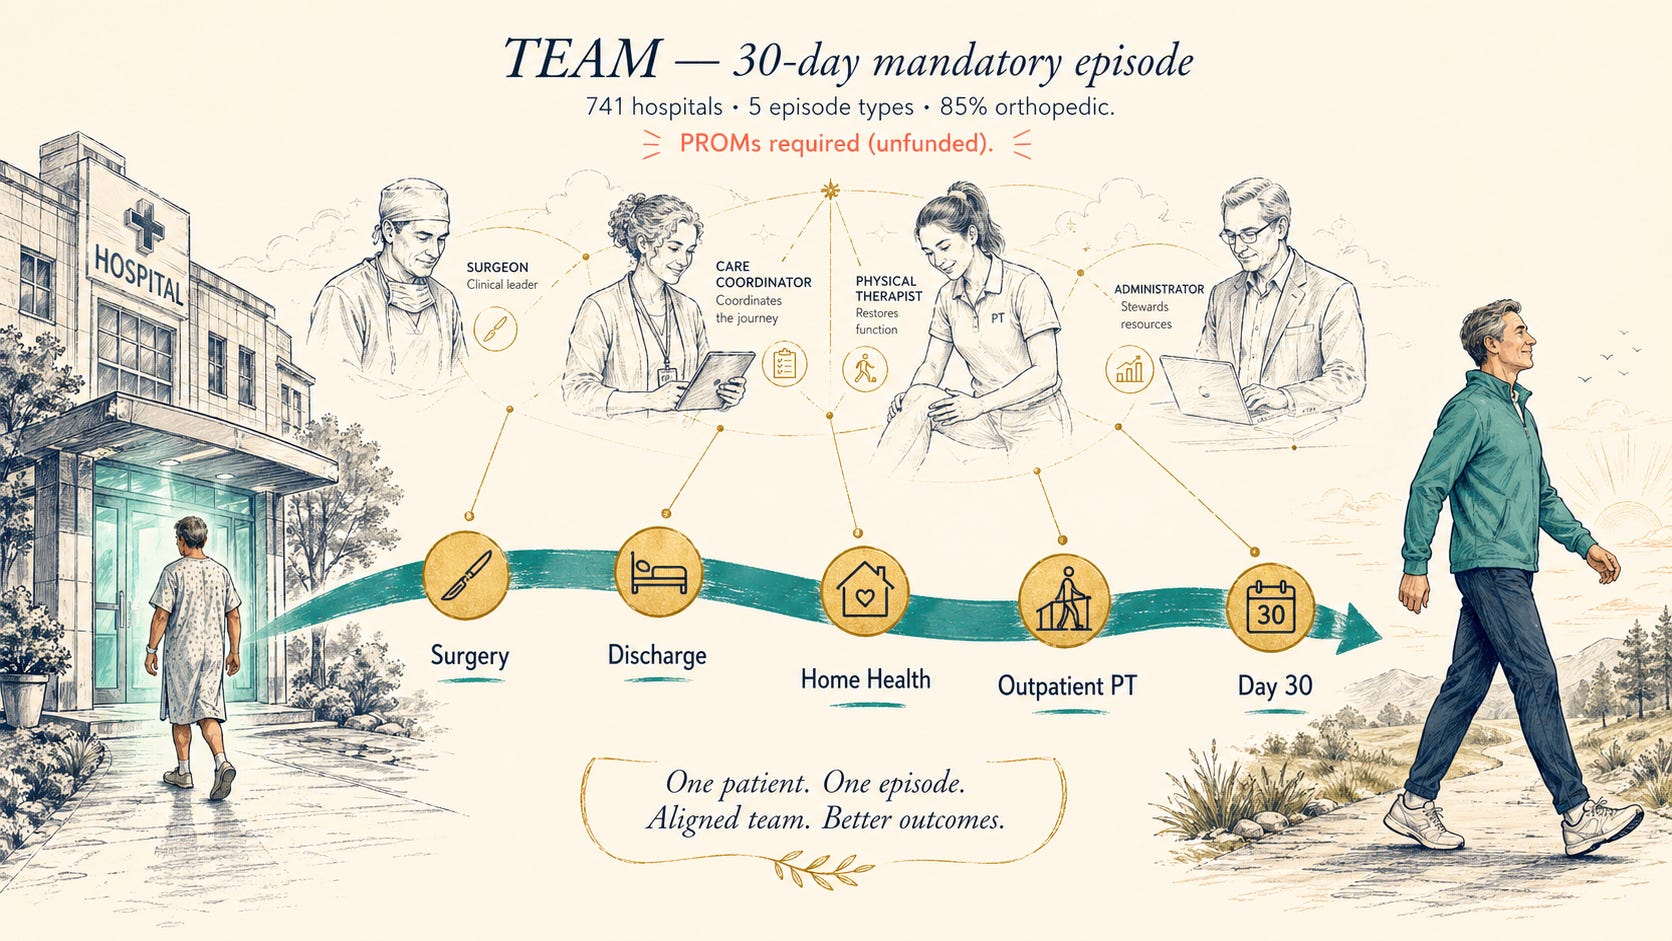
TEAM (Transforming Episode Accountability Model) is the most immediately consequential for orthopedic care. It launched January 1, 2026, as a mandatory model requiring 741 hospitals in selected Core Based Statistical Areas to accept financial responsibility for surgical episodes spanning the procedure through 30 days after discharge.¹⁹ Three of the five episode categories are orthopedic: lower extremity joint replacement, surgical hip and femur fracture treatment, and spinal fusion. An estimated 85% of TEAM episodes are expected to involve orthopedic procedures.²⁰
Hospitals receive a target price that covers the inpatient stay, postacute care (skilled nursing, home health, outpatient therapy), and followup visits. TEAM creates a gainsharing framework allowing hospitals to share savings and losses with “TEAM collaborators,” a category that includes physicians, group practices, and other providers involved in managing the episode.²¹ This is the formal mechanism through which a physical therapy group could become a financially aligned partner in episode management rather than simply a downstream referral destination.
TEAM also requires patient reported outcome measures (PROMs) but provides no financial support for the infrastructure to collect them.²⁰ That unfunded mandate is worth keeping in mind. It creates a real infrastructure gap and, for organizations that can fill it, a meaningful role.
CJR-X: The Nationwide Successor Arrives
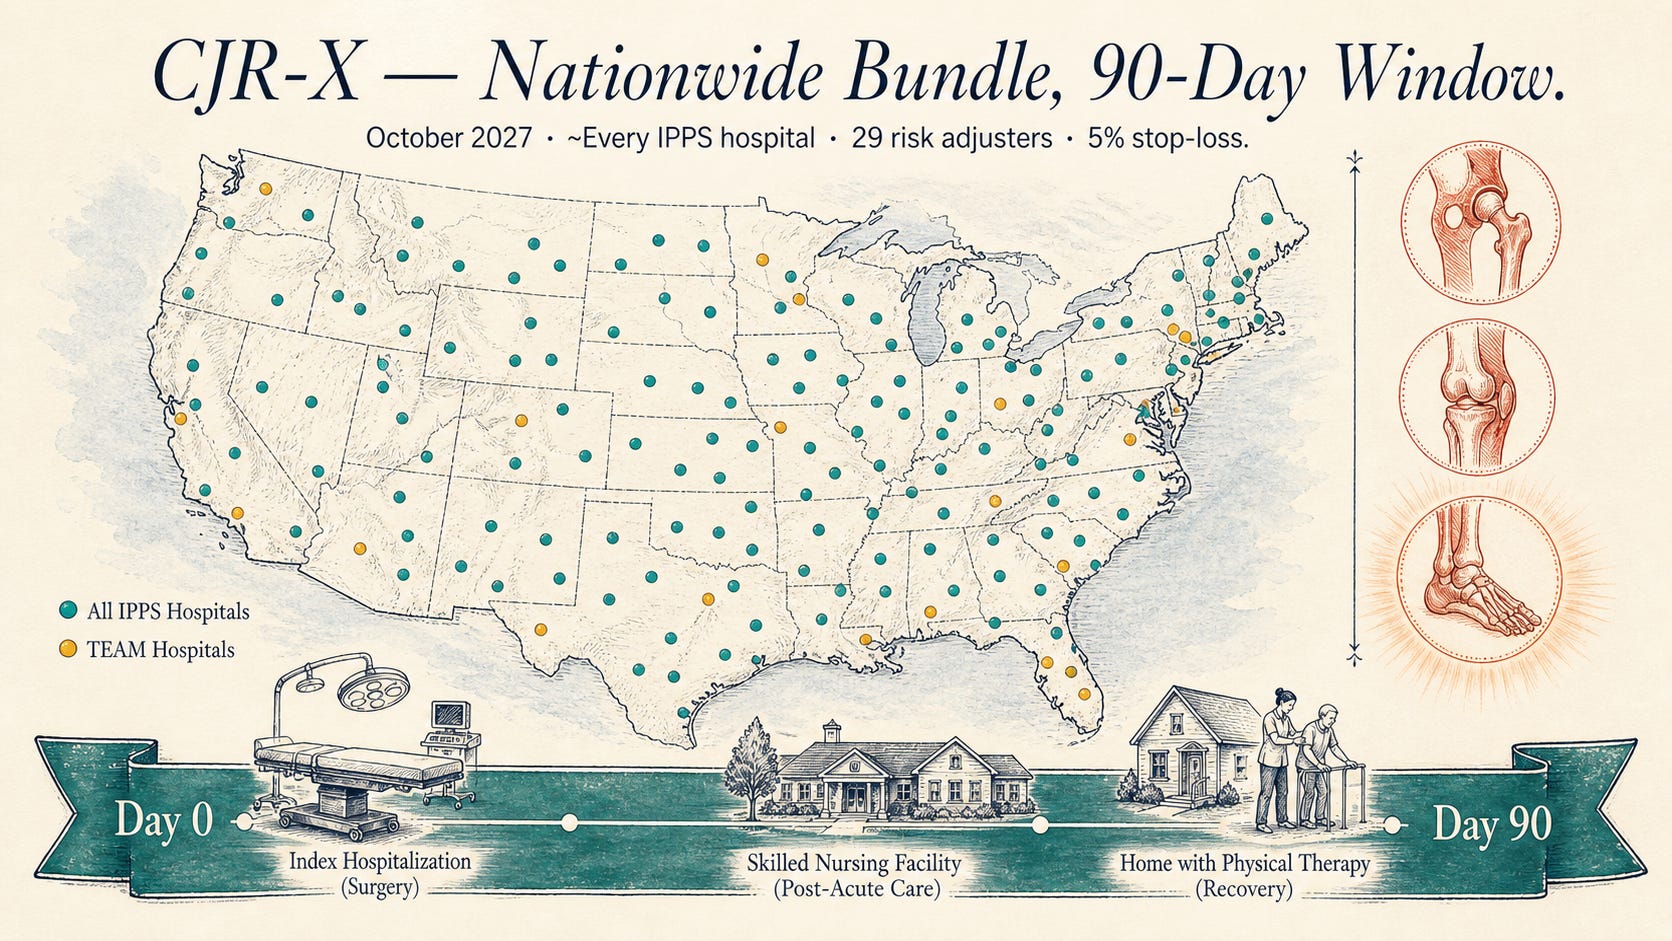
If TEAM was the first wave, CJR-X (Comprehensive Care for Joint Replacement Expanded) is the tide coming in behind it. Proposed on April 10, 2026 in the Fiscal Year 2027 Hospital Inpatient Prospective Payment System (IPPS) proposed rule, CJR-X would be the first nationwide test of a mandatory episode based payment model and would begin October 1, 2027, with public comment open through June 9, 2026.³⁹˒⁴⁰˒⁴¹
The operational contours matter, because they both extend and diverge from TEAM in ways that reshape the MSK episode economy.
First, CJR-X is nationwide. Nearly every IPPS hospital in the country would be required to participate. The exclusions are narrow: critical access hospitals, rural emergency hospitals, Maryland hospitals (carved out under the state’s all-payer rate-setting model), and the approximately 700 hospitals currently in TEAM, which remain on TEAM through its 2030 expiration before transitioning to CJR-X in 2031.³⁹˒⁴⁰ For nearly everyone else, mandatory bundled payment for lower extremity joint replacement is coming.
Second, CJR-X expands the procedure set and the episode window. Like the original CJR (which concluded in 2024 after generating an estimated $112.7 million in net savings in performance years 6 and 7 while maintaining quality), CJR-X covers hip and knee replacements, but it adds ankle replacement — a meaningful expansion that folds foot and ankle surgery into the bundled payment architecture for the first time.³⁹˒⁴¹ And it covers episodes performed in both inpatient and outpatient hospital settings, reflecting the reality that a growing share of LEJR is migrating to HOPDs. The episode window is 90 days post discharge rather than TEAM’s 30 days, giving hospitals meaningfully greater exposure to skilled nursing stays, home health, outpatient rehabilitation, and readmissions.³⁹
Third, the risk adjustment methodology is more sophisticated. CJR-X incorporates 29 risk adjusters, and the proposed rule includes a 5% stop loss protection for lower-resourced rural and safety-net hospitals to prevent the model from disproportionately penalizing facilities that serve higher-acuity populations.⁴⁰
Taken together, CJR-X signals two things. The first is CMS’s long-term intent: mandatory episode accountability for joint replacement is not a pilot, and it is not regional. It is becoming the default. The second is that the post-acute care corridor is now the battleground. A 90 day window turns every discharge decision — skilled nursing vs. home health vs. outpatient PT, length of stay at each step, readmission prevention — into a financial lever. Hospitals without a coordinated post-acute and rehabilitation strategy are going to feel this acutely. Hospitals with one, ideally built around a technology-enabled PT co-management partner, will convert that same 90 day window into shared savings.
For orthopedic surgeons specifically, CJR-X creates new opportunities and new pressures simultaneously. The gainsharing mechanism (like TEAM’s) allows surgeons to participate in episode savings as collaborators. But the pressure on facility fees, implant costs, and post-acute utilization is going to intensify, and the surgeon-hospital conversation about implant selection, ASC vs. HOPD site of service, and discharge planning is going to become more contested. Ankle replacement surgeons in particular should pay close attention, a procedure that has never been bundled is about to be.
ACCESS: The Chronic Care Side of the Architecture
ACCESS (Advancing Chronic Care with Effective, Scalable Solutions) is a ten year voluntary program beginning July 5, 2026, that tests outcome aligned payments for technology supported chronic care management.²² Its MSK track focuses specifically on chronic musculoskeletal pain lasting more than three months, with outcomes measured through validated patient reported assessments of pain intensity, interference, and overall function.²³
The MSK track operates on a single 12 month care period with no continuation phase, paying participants a fixed annual amount of $180 per beneficiary.²⁴ ACCESS also requires participants to screen for health related social needs (HRSNs), establish referral pathways to community resources, and track referral completion.²⁵ And it creates a comanagement payment of approximately $100 per year per beneficiary for primary care clinicians who review electronic care updates and document care coordination actions, without beneficiary cost sharing.²⁶
The HRSN screening requirement deserves attention. For MSK populations, the social determinants that matter most include fall risk, home safety, and access to exercise and rehabilitation. Screening for these needs and then closing the loop with referrals for things like home modifications and bone health services is the kind of upstream intervention that could prevent the acute events these other models are designed to manage.
The rest of this essay is where I see things clicks into place. The landscape of the problem, the reimbursement paradox that’s been quietly reshaping orthopedics for two decades, and the three models that now sit on top of the MSK surgical and chronic care continuum: TEAM, the newly proposed CJR-X, and ACCESS.
LEAD’s ten year ACO design and why its benchmark stability fundamentally changes the MSK investment case
ASM’s ambulatory specialty model and what it means for low back pain, PM&R, pain management, and the specialists whose cost scores depend on PT
The RISE falls prevention episode — CMS’s first structured Medicare pathway for home modification as medicine, with a $2,500 per beneficiary benefit
The PT co-management design pattern that lets a single physical therapy partner operate as a clinical services layer across TEAM, CJR-X, ACCESS, LEAD, and ASM simultaneously
How the models connect, including why LEAD is the natural evolution of TEAM and why CJR-X creates a new urgency for ACO–hospital integration
The Rocky Road Ahead — the open questions about ACCESS payment adequacy, LEAD adoption among smaller ACOs, AI inferred risk adjustment, CJR-X’s comment period politics, and the sustainability of TJA reimbursement
Practical Considerations for health systems, ACOs, PT groups, and MSK specialists — the operator-level implications
Interactive ASM Financial Dashboard: See what providers and organizations have been selected for the ambulatory specialty model and the projections of risk and upside considerations based on Part B Billing.
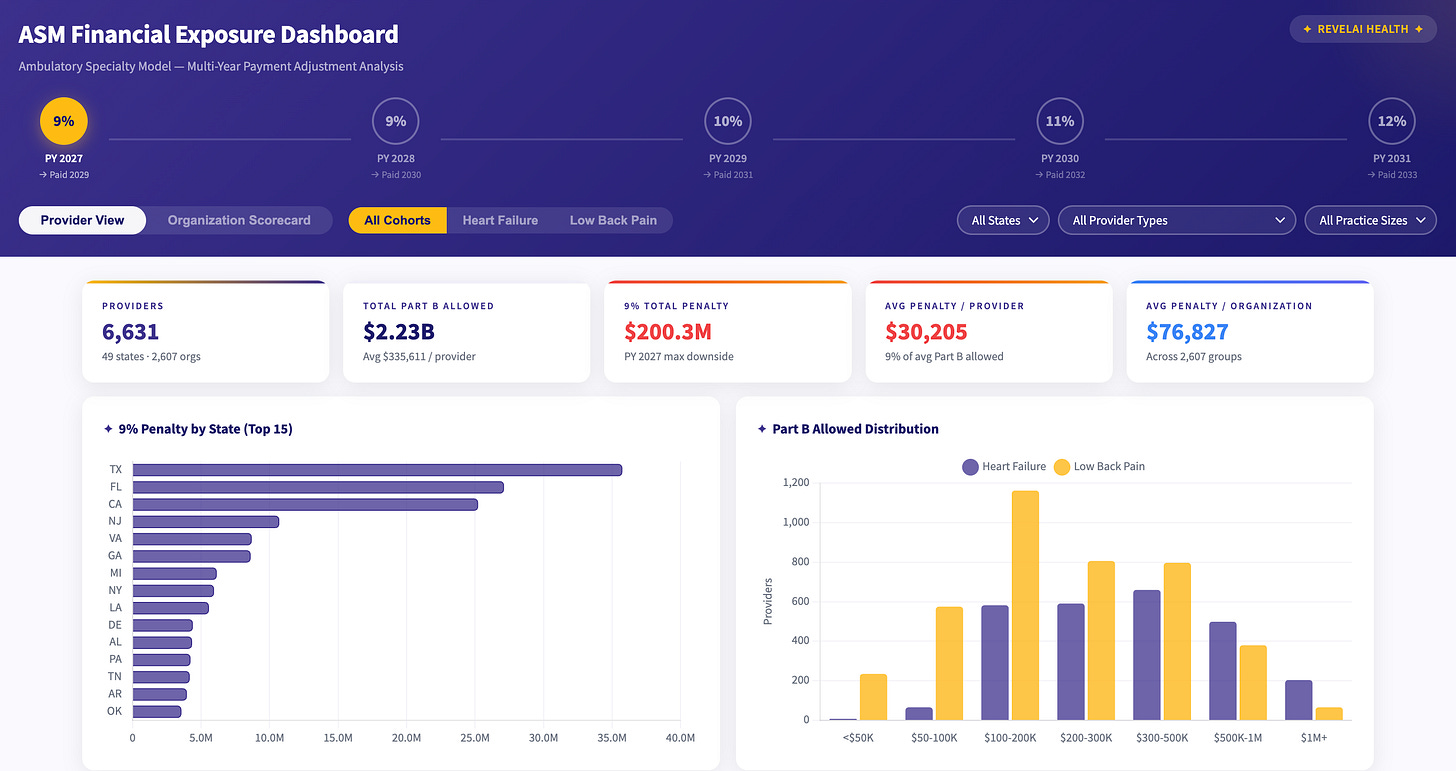
Interactive ASM Financial Dashboard: See what providers and organizations have been selected for the ambulatory specialty model and the projections of risk and upside considerations based on Part B Billing.
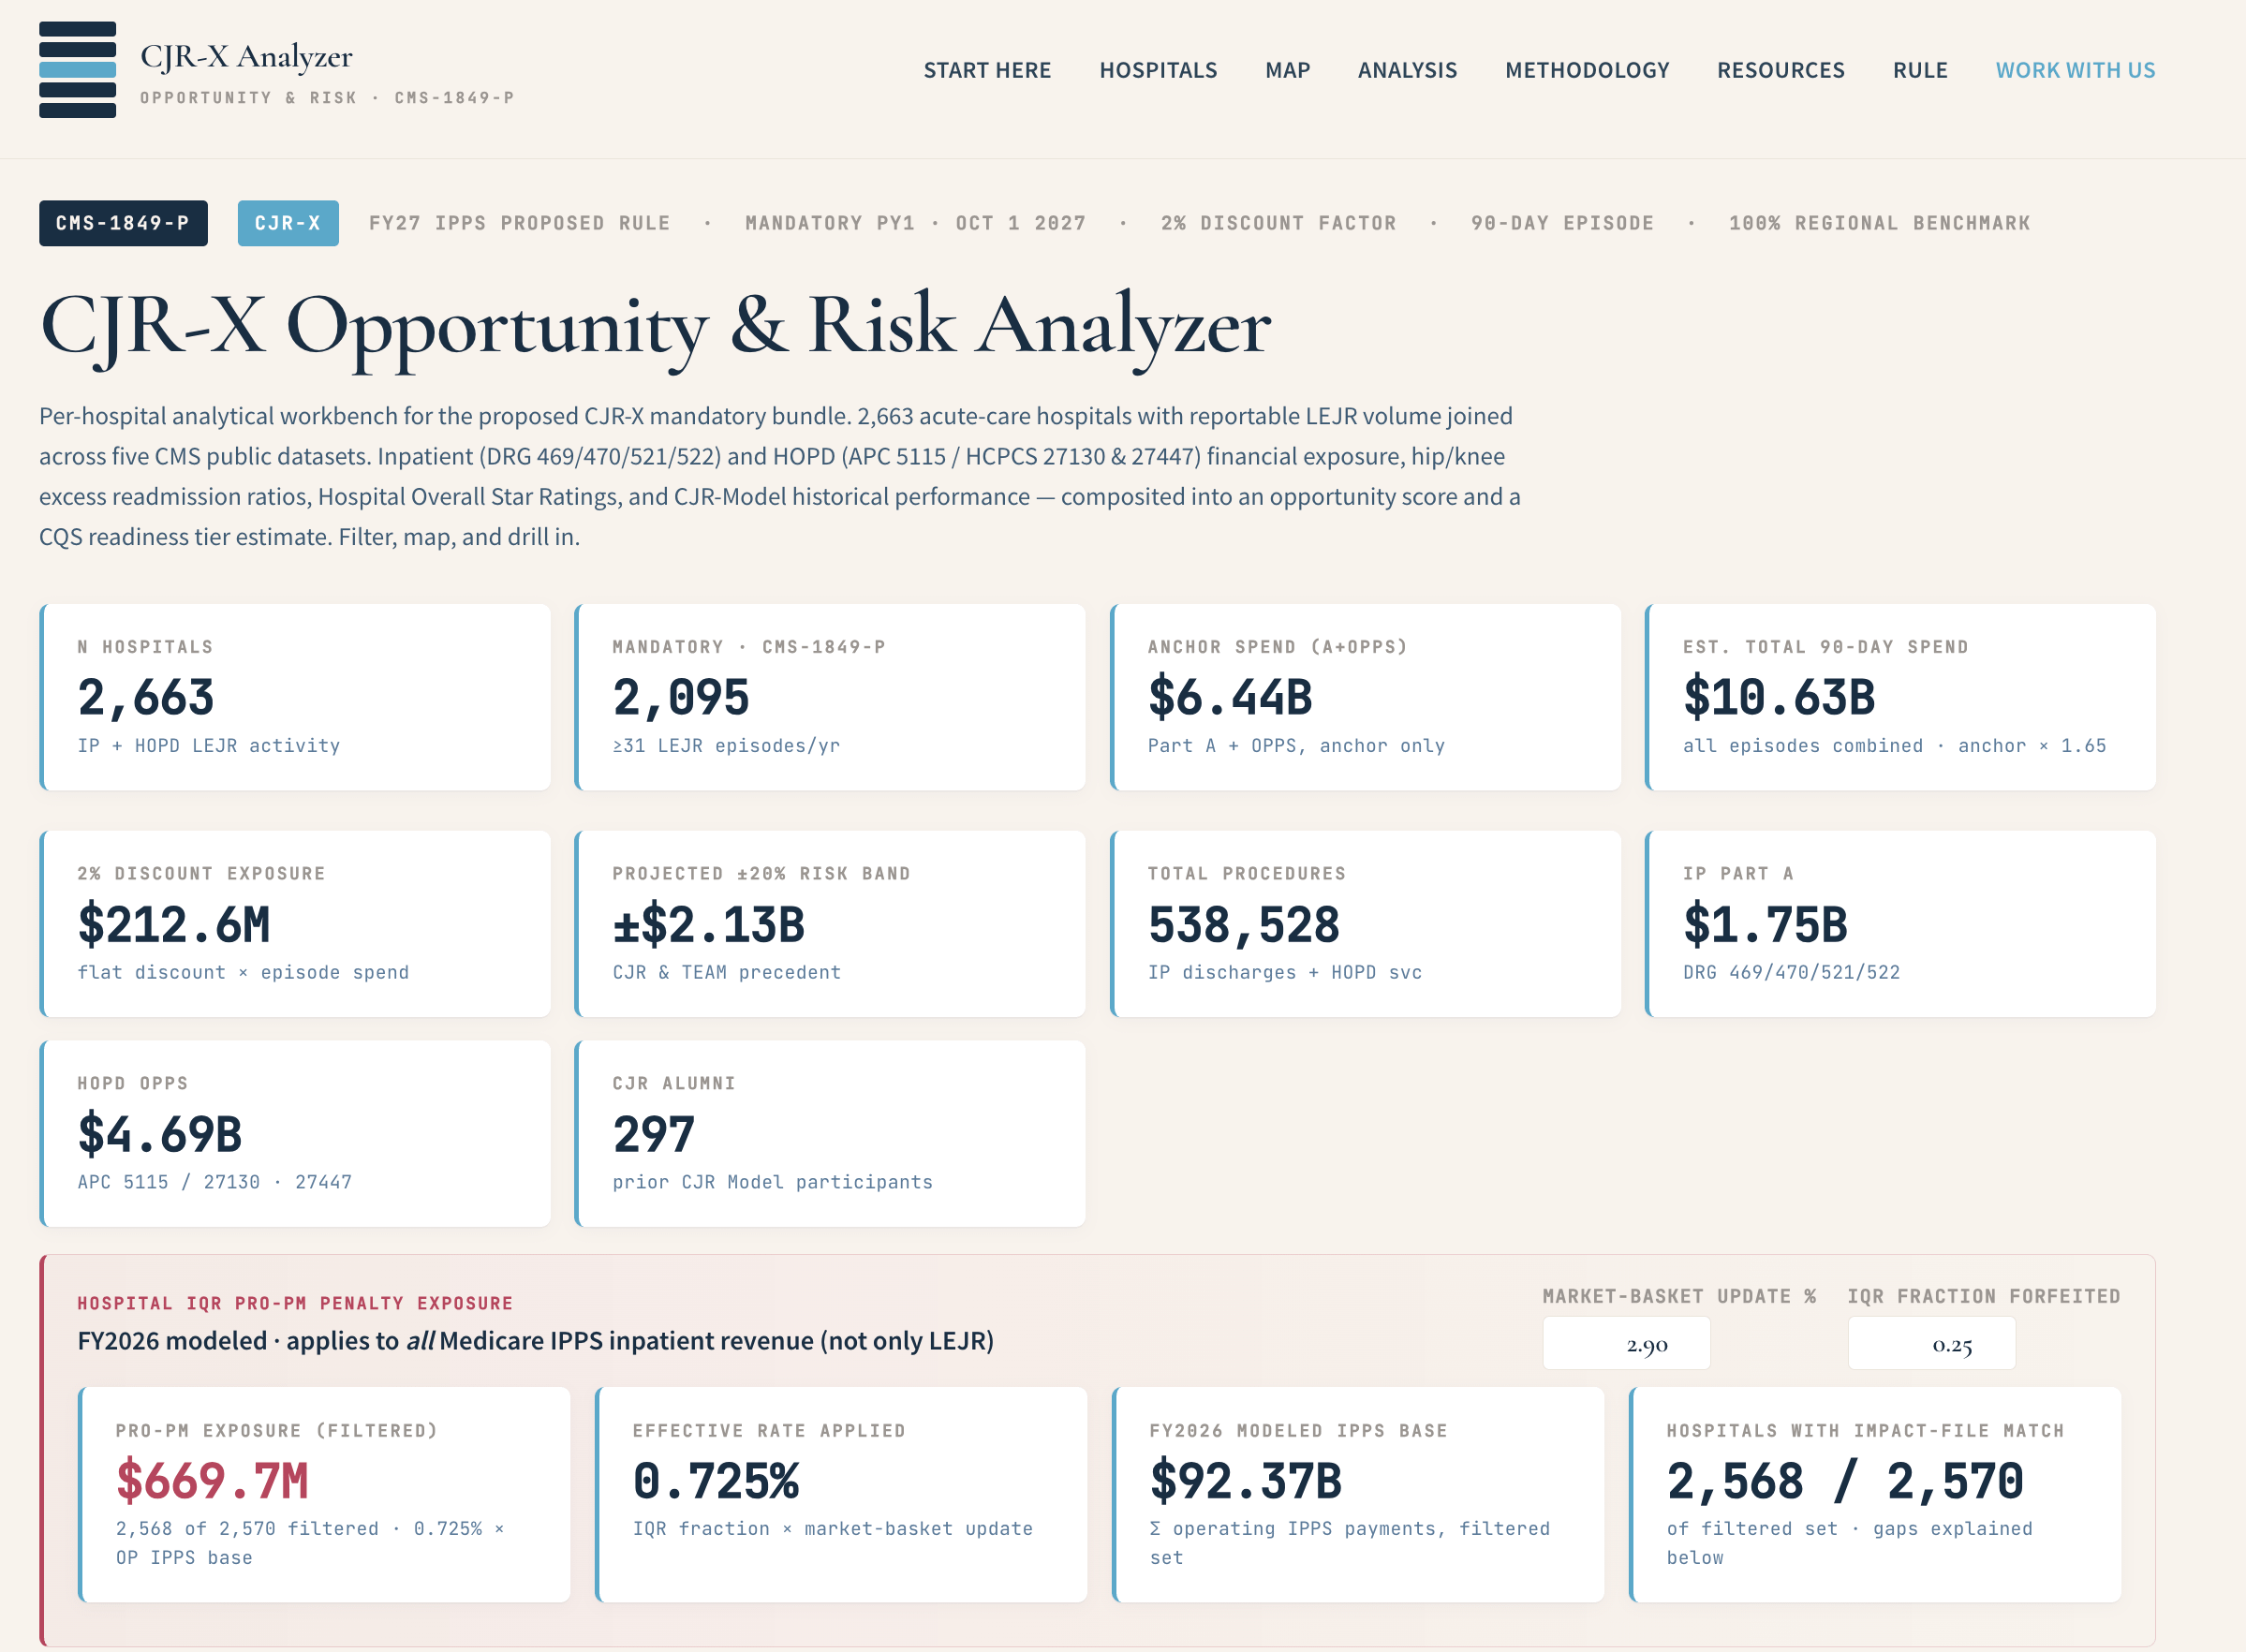
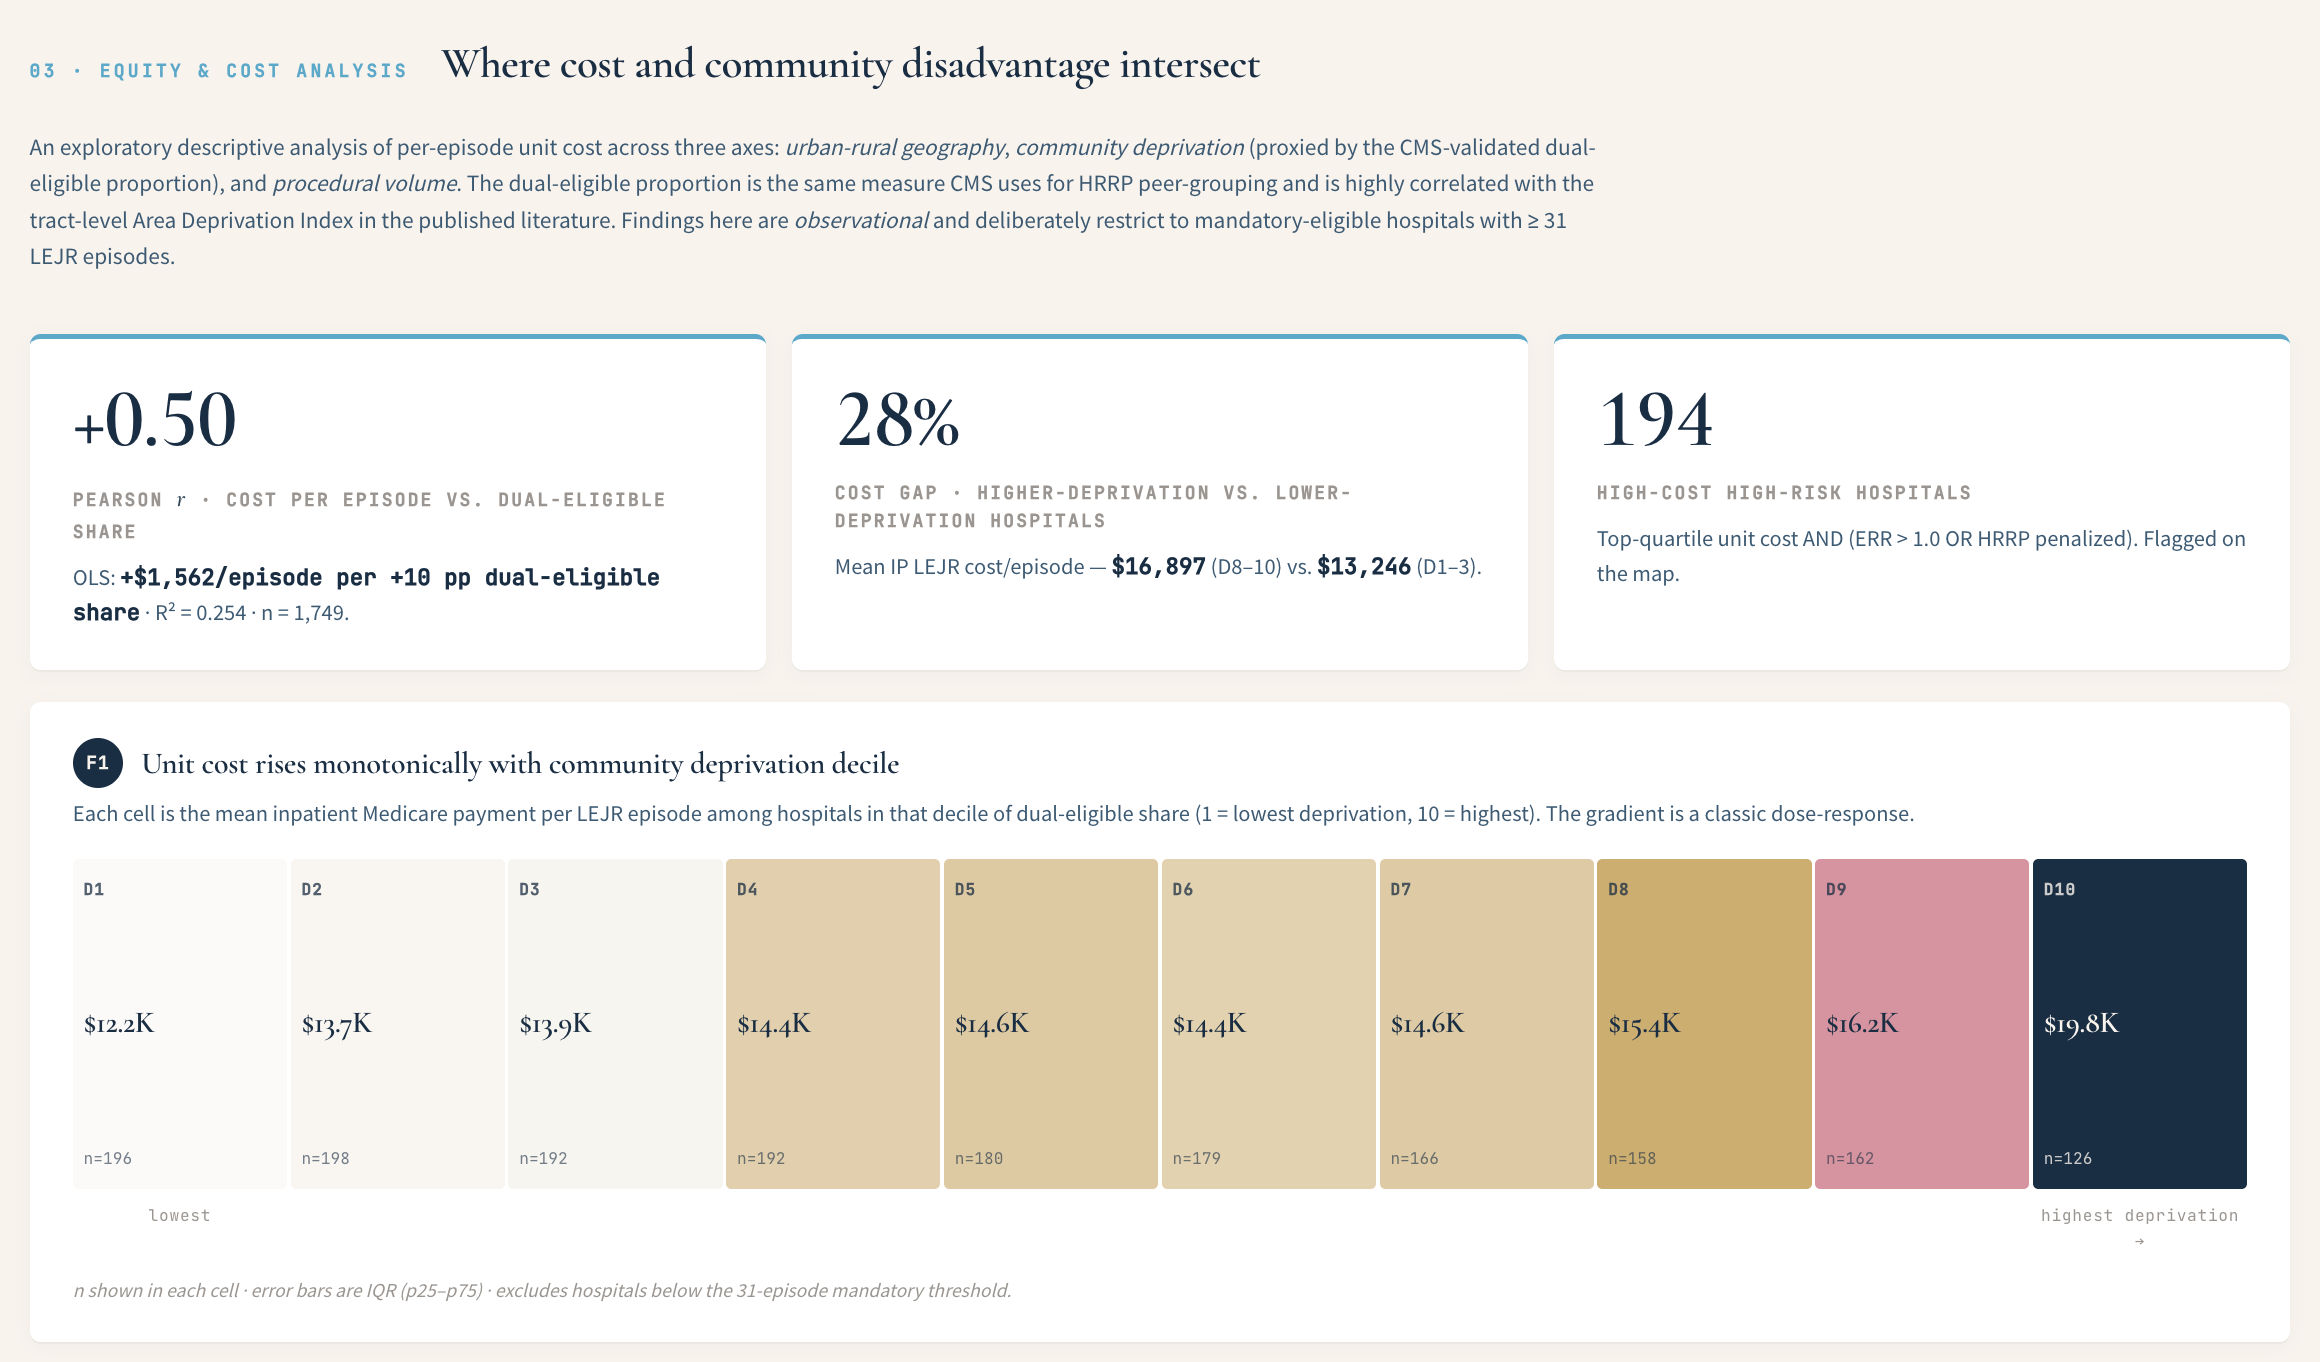
Interactive CJR-X and Total Joint Replacement Bundle Explorer: I combined Part A billing, previous CJR hospital performance and HRPP penalties to create a map of high risk cost hospitals and projected penalties (estimates only based on available public Part A data).


Being a Techy Surgeon Subscriber.
The full archive of deep dive policy analyses — every major CMS model as it drops, every Innovation Center signal worth tracking, written for clinicians and operators, not consultants
Techy Flows tutorials — practical, step-by-step agentic AI workflows for physicians, surgeons, and health system teams. Real prompts, real automations, real throughput wins
Techy Health chat — the subscriber community where I answer questions, field thorny policy or AI implementation challenges, and share breaking news as it lands
Breaking news on AI features, model releases, and healthcare AI tooling — what actually matters for clinicians and operators, filtered and translated
Practical workflows and operator-ready frameworks — the infrastructure, templates, and playbooks I use in my own work at RevelAi Health and Duke
The Rest of the Architecture
LEAD: The Long-Horizon ACO
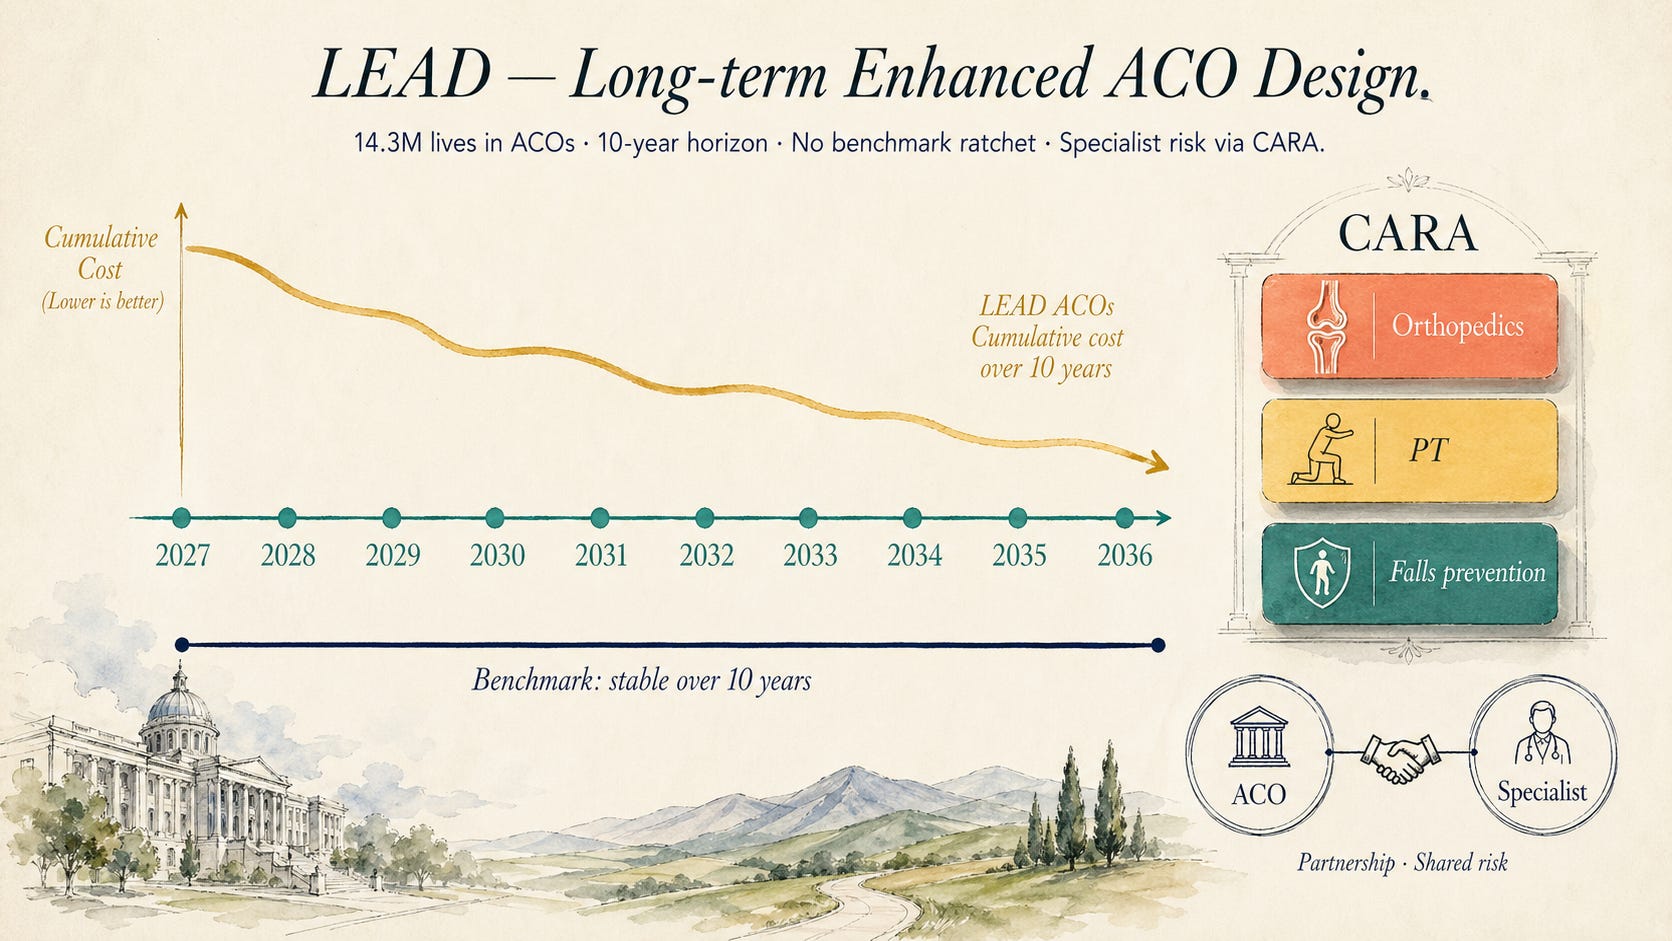
LEAD (Long term Enhanced ACO Design) launches January 1, 2027, as a decade long voluntary ACO program.²⁷ Its most significant structural feature is that benchmarks do not reset over the ten year duration. An ACO that reduces costs in year three will not face a lower benchmark in year four.²⁸ This addresses the ratchet problem that has undermined sustained investment in prior ACO models.
The feature most relevant to MSK care is CARA (CMS Administered Risk Arrangements), a platform designed to facilitate downstream, episode based risk arrangements between ACOs and specialists.²⁷ CARA allows ACOs to structure risk sharing with orthopedic surgeons, physical therapists, and other specialists through a CMS mediated framework. ACOs can either adopt predetermined CMS constructed episodes or create novel constructs through negotiation with their preferred providers.²⁹ The CARA episode types under consideration span cardiovascular procedures, general surgery, urology, ophthalmology, gastroenterology, and vascular access, but the most novel offering is a falls prevention episode I’ll discuss in detail below.²⁹
As of January 2026, 14.3 million Medicare beneficiaries receive care coordinated by ACOs, and LEAD applications remain open through May 17, 2026.³⁰
A candid note on LEAD adoption: having spoken with several ACOs, the appetite for transitioning from MSSP to LEAD is more cautious than the model’s design might suggest. Smaller and rural ACOs in particular find the operational complexity daunting. Seventy seven percent of ACOs already operate across six or more EHRs, and LEAD’s requirements for specialist risk arrangements through CARA add another layer of administrative infrastructure.³¹ There are also concerns about AI inferred risk adjustment and the transparency of benchmarking methodology.³² MSSP to LEAD transitions appear unlikely for many organizations in the near term, which means LEAD’s specialist integration benefits may initially accrue to larger, more operationally sophisticated ACOs. That said, CMS has signaled that LEAD is designed to expand participation by addressing the financial and administrative barriers that have kept smaller and rural practices out of prior models. A good way to identify ACOs that will almost certainly be in LEAD, is to look at a map of current REACH ACOs.
ASM: Ambulatory Specialty Accountability

ASM (Ambulatory Specialty Model) begins January 1, 2027, as a mandatory model targeting ambulatory specialists managing heart failure and low back pain.³³ The MSK relevant specialties, including orthopedic surgery, pain management, physical medicine and rehabilitation, and anesthesiology, will have their fee for service payments adjusted based on episode based cost measures (EBCMs), with a minimum threshold of 20 attributed episodes per performance year.³⁴
The low back pain episode is particularly important in this context. Quality measures for ASM’s LBP track include functional status change and imaging appropriateness, metrics that directly reflect the kind of conservative, function focused management that physical therapy provides.³⁵ CMS declined to include physical therapists as direct ASM participants (citing Medicare specialty code limitations), but the specialists who are included, orthopedic surgeons, PM&R physicians, pain management specialists, are precisely the clinicians whose downstream referral patterns and episode costs PT partners influence most directly.³⁵ A PT group functioning as a clinical services partner for an ACCESS participant is, in practice, an essential part of the care team whose work determines whether the ASM accountable specialist meets cost and quality targets.
See the interactive dashboard here of compiled provider and organization projected penalties exclusive for Techy Surgeon Subscribers.
The RISE Episode: Falls Prevention Inside LEAD
The LEAD RFA describes a CARA episode offering that I think deserves considerably more attention than it has received. It’s called RISE to Age in Place, Resilience and Independence in a Safe Environment, and it represents something genuinely new in Medicare payment: a structured, episode based approach to falls prevention with a home modification benefit.²⁹
The RISE episode works as follows. An initial screening assessment determines beneficiary eligibility and care needs. Following that evaluation, an interdisciplinary care team comprising occupational therapists and registered nurses delivers comprehensive falls prevention interventions: risk assessments, medication management, strength training, balance exercises, and healthcare provider communication plans. The interventions are home based and time limited, designed to improve a patient’s functional safety in their home environment.²⁹
Two structural features distinguish RISE from other CARA episodes. First, it operates without a target price. Instead, participating entities bill Level II HCPCS codes (nonpayable, zeroed out G codes) for a bundle of OT and RN services through Medicare Shared Systems to receive a prospective payment, stratified by beneficiary acuity level.²⁹ This is important because it means RISE doesn’t require the actuarial complexity of target price negotiation that characterizes the EBCM based episodes, lowering the barrier to participation.
Second, RISE includes a home modification benefit of up to $2,500 per beneficiary. When structural improvements are warranted to reduce fall risk (grab bars, lighting modifications, stair rails), the RISE team, in partnership with the ACO, can engage a handyperson to deliver targeted modifications. CMS expects to make a determination that the Anti Kickback Statute safe harbor for CMS sponsored model patient incentives (42 CFR § 1001.952(ii)) is available to protect these modifications, treating them as in kind remuneration similar to the GUIDE Model’s Environmental Modification Benefit.²⁹ The ACO pays for the modifications, not the Trust Fund.
For anyone who treats hip fractures, and I treat them regularly, this is a meaningful development. The economics are stark: a home modification that costs $500 to $2,500 can prevent a fracture that costs $50,000 to treat and increases the patient’s eight year mortality risk by 83%.⁸˒⁹ RISE creates a structured mechanism to fund that prevention within Medicare’s payment architecture, rather than leaving it to the fragmented landscape of community grants and Medicaid waivers.
ACOs that implement the RISE episode satisfy LEAD’s Population Quality Plan (PQP) requirement, the mandate to develop structured prevention interventions for their attributed population. The RISE episode costs are included in the ACO’s total cost of care for final financial settlement, and savings generated from reduced falls can be shared between the ACO and the downstream RISE entity.²⁹

The PT Comanagement Partner as Clinical Services Layer
The design pattern we’re building around at RevelAi Health is straightforward in concept, even if the operational details are complex.
An ACCESS participant serving as the digital enrollment, engagement, and AI coaching platform handles intake, HRSN screening, PROM collection, fall risk identification, bone health gap detection, and care navigation across the team. This is the technology layer: the infrastructure that identifies patients, stratifies risk, measures outcomes, guides patients through their care, and satisfies reporting requirements across ACCESS, TEAM, CJR-X, and LEAD simultaneously.
A physical therapy comanagement partner serves as the clinical services entity. This is not a new idea in itself. PT groups have always been part of the postacute care landscape. What is new is the payment architecture that makes them a financially aligned partner across multiple care contexts simultaneously.
Under ACCESS, the PT partner provides clinical escalation for chronic MSK patients whose pain requires direct intervention beyond digital management. Under TEAM and, beginning in 2027, CJR-X, the same PT partner delivers prehabilitation to optimize surgical candidates and manages structured rehabilitation across the 30 day (TEAM) or 90 day (CJR-X) post-discharge window to reduce readmissions and skilled nursing facility utilization. Under LEAD’s RISE episode, PT and OT providers deliver the falls prevention interventions, strength training, balance exercises, risk assessments, that constitute the core clinical service. Under ASM, the PT partner’s work directly determines the functional status outcomes and cost efficiency that LBP episode specialists are measured on.
The financial alignment runs through multiple channels: TEAM and CJR-X gainsharing for episode savings, ACCESS comanagement payments for documented care coordination, direct billing for therapeutic services as substitute spend within both bundles, and prospective payment through RISE’s G code structure for falls prevention. A PT group that can operate across all of these simultaneously, collecting PROMs, coordinating with referring clinicians, reporting outcomes in standardized formats, becomes an essential component of the value based MSK care infrastructure.
This is also where the ASM low back pain episode dovetails particularly well. The specialists accountable under ASM, orthopedic surgeons, PM&R physicians, pain management specialists, depend on PT to deliver the conservative management, functional restoration, and imaging avoidance protocols that determine their episode cost scores. A PT group empowered by an ACCESS participant’s digital infrastructure can provide these services with the kind of structured outcome measurement that makes the value visible to everyone in the arrangement.

Bone health and annual wellness visits. The annual wellness visit remains one of Medicare’s most underutilized preventive touchpoints and a natural venue for osteoporosis screening, fall risk assessment, and bone health management. A technology enabled system that prompts AWV scheduling, prepopulates screening tools, and tracks referral completion addresses care gaps that compound over years into the fractures and surgical episodes these models manage. For LEAD ACOs, particularly those implementing RISE, this kind of upstream investment in bone health (DXA screening referrals, medication adherence monitoring for osteoporosis treatments, vitamin D and calcium supplementation tracking) directly reduces total cost of care against benchmarks that won’t ratchet down.
How the Models Connect: A Layered MSK Architecture
TEAM mandates participation for hospitals in selected CBSAs beginning 2026. CJR-X extends mandatory joint replacement accountability to essentially every IPPS hospital nationwide beginning October 2027, with a longer 90 day episode window. LEAD invites ACOs to take decade long population risk with stable benchmarks beginning 2027. Many patients undergoing TEAM or CJR-X episodes are simultaneously attributed to ACOs, meaning the hospital’s episode cost is also part of the ACO’s total cost of care.
This creates natural alignment. An ACO participating in LEAD has a financial interest in reducing both the frequency and the cost of surgical episodes at its affiliated TEAM and CJR-X hospitals. The mechanisms for doing so are the kinds of upstream prevention and chronic care management that ACCESS and RISE enable: chronic pain management, fall prevention, bone health screening, prehabilitation.
CARA makes this operational. An ACO uses LEAD’s risk arrangement platform to structure episode based sharing with orthopedic specialists and PT groups. The ACO invests in population health and RISE falls prevention; the hospital optimizes episode efficiency under TEAM and CJR-X; the PT partner delivers preoperative, perioperative, and postoperative care with measurable outcomes.
LEAD feels like a natural evolution of the TEAM and CJR-X concept. If TEAM and CJR-X hold hospitals accountable for episodes, LEAD holds the broader care community accountable for the population from which those episodes arise. Hospitals tied to ACOs, especially ACOs entering LEAD, become natural partners for integrated MSK care coordination. The ACO needs its specialists and community partners to reduce avoidable episodes; the hospital needs its ACO partners to manage patients upstream. With CJR-X’s 90 day window, the downstream post-acute exposure is materially larger than under TEAM, making the ACO–hospital alignment even more consequential.
And the RISE episode makes this concrete in a way that prior ACO models never did. Rather than asking ACOs to figure out falls prevention on their own, CMS has built a structured episode with defined interventions, a payment mechanism, and a home modification benefit. An ACO can partner with a PT/OT entity to deliver RISE interventions, use an ACCESS participant’s technology infrastructure to identify eligible beneficiaries and track outcomes, and see the savings reflected in both the RISE episode settlement and the ACO’s total cost of care benchmark.
The Rocky Road Ahead
I still have some important questions without clear answers yet.
ACCESS MSK track payment adequacy. At $180 per year per beneficiary, the MSK track is the lowest paid ACCESS pathway. Whether that covers the infrastructure costs of technology enabled care management, including HRSN screening and navigation, depends on patient volume and the degree to which shared infrastructure across ACCESS tracks reduces per track costs. I don’t think anyone can answer this confidently until the first cohorts have completed a care period, but my belief is that ACCESS will be a wedge for tech companies to other paid value based contracts that expand the scope of what ACCESS participants will offer beyond a digital health benefit.
CJR-X comment period and final rule risk. CJR-X is currently in the IPPS FY27 proposed rule stage, with public comment open through June 9, 2026.⁴¹ Between now and the final rule, every major hospital trade association, specialty society, and post-acute lobby will weigh in. Expect pressure to narrow the mandatory scope, soften the risk adjustment methodology, expand the stop-loss protections, and delay the October 2027 start. Some of that pressure will be legitimate; some will be rent-seeking. The shape CJR-X takes in the final rule will determine whether it becomes the quiet, coherent successor to CJR/TEAM or whether it gets carved into something less ambitious. Operators should track the final rule closely rather than building strategy around the proposal text.
LEAD adoption among smaller ACOs. The operational burden of LEAD, including CARA implementation, specialist risk arrangements, and PQP development, may be too heavy for smaller and rural ACOs that are already stretched thin managing MSSP requirements across fragmented EHR environments. CMS has designed LEAD to lower barriers, but the gap between policy design and operational reality remains wide for organizations without dedicated value based care infrastructure. MSSP to LEAD transitions will likely be slow and selective. I think a massive educational campaign from the conveners like Wellvana and Aledade will be needed given the short time horizon to the application deadline.
AI inferred risk and benchmarking transparency. ACOs I’ve spoken with express concern about the use of AI in risk adjustment and the opacity of benchmarking methodology under new models. The WISeR model’s introduction of AI assisted utilization review has heightened anxiety about algorithmic decision making in Medicare.³⁶ These concerns are not unique to LEAD, but they add friction to adoption.
CARA and RISE operational readiness. The LEAD RFA describes CARA and RISE at a detailed conceptual level, but CARA episodes don’t begin triggering until January 2028, a full year after LEAD launches.²⁹ The success of episode based specialist risk sharing depends on whether CMS’s implementation timeline holds and whether the 4i platform for episode risk parameter submission functions smoothly.
Political durability. TEAM is mandatory and codified in regulation, making it relatively durable. CJR-X is in proposed rule stage — still codifiable but not yet final. ACCESS and LEAD are voluntary and newer, which makes them more susceptible to strategic shifts. The current Innovation Center leadership has emphasized evidence based prevention and beneficiary empowerment, and the MAHA ELEVATE model’s focus on lifestyle interventions could complement or compete with ACCESS’s chronic care approach.³⁷˒³⁸
The sustainability question. If TJA reimbursement continues its current trajectory, we will reach a point where the most cost effective intervention in orthopedics is not financially viable for the surgeons and hospitals that deliver it.¹³ The models described here create mechanisms for value capture beyond the procedure itself, through episode management, chronic care coordination, and population health. Whether those mechanisms generate enough revenue to offset the continued erosion of procedural reimbursement is an open and important question.
PT group readiness. The design pattern I’ve described requires physical therapy practices to function as data driven, technology enabled comanagement entities capable of collecting PROMs, coordinating care across models, and operating in gainsharing arrangements. That is a significant step beyond what most practices do today. With CJR-X expanding the bundled addressable market from 741 TEAM hospitals to essentially every IPPS hospital in the country, the commercial opportunity for PT groups that are ready is an order of magnitude larger. The partnerships that work will require investment in care coordination infrastructure and population health analytics, capabilities that platforms like MSK Access are designed to provide, but that many groups are still developing independently.
Practical Considerations
For health systems under TEAM and, soon, CJR-X, the near term priority is post-acute care navigation and PROMs collection infrastructure. It’s required for TEAM regardless, and the same system feeds ACCESS outcome measurement and LEAD quality reporting. With CJR-X on the horizon, the 90 day post-discharge window makes this infrastructure investment even more consequential. Partnering with PT groups and digital health platforms to provide this as a service may be more practical than building internally. Start scenario-planning now for CJR-X’s October 2027 start, especially for the cost categories most exposed to a 90 day window: SNF utilization, home health intensity, outpatient therapy duration, and 90 day readmissions.
For ankle replacement surgeons and foot and ankle programs, CJR-X is the first time your procedure has been placed inside a mandatory bundle. Build relationships now with PT partners who can deliver standardized prehab and postop protocols for ankle arthroplasty, and start tracking 90 day episode costs internally so you understand your baseline before the target price methodology is finalized.
For ACOs evaluating LEAD, examine your attributed population’s MSK burden directly. What proportion of your beneficiaries have chronic MSK pain? What is their fall risk profile? What are your AWV completion rates? Consider whether the RISE episode could serve as your PQP intervention. It provides a structured, CMS defined pathway for falls prevention that satisfies the requirement while generating measurable savings. And be realistic about CARA readiness: episode triggers begin in 2028, which means 2027 is a planning year.
For PT groups and MSK specialists, the opportunity is to demonstrate value as a clinical services layer that operates across chronic care, surgical episodes (TEAM and CJR-X), falls prevention, and ambulatory specialist support simultaneously. That means investing in the technology and workflows to collect PROMs, coordinate with referring physicians, and report outcomes in formats that TEAM hospitals, CJR-X hospitals, LEAD ACOs, and ASM accountable specialists can all use.
The underlying logic is not complicated: a bone density deficit that costs $200 to screen for becomes a fracture that costs $50,000 to treat. A home modification that costs $2,500 under RISE prevents a hip fracture that increases mortality risk by 83%. A chronic pain patient managed proactively through ACCESS is a surgical episode prevented under TEAM or CJR-X, a cost avoided for LEAD, and a quality metric improved for ASM.
CMS has built the models. The work now is connecting them in practice.
Christian Pean, MD, MS is an orthopedic trauma surgeon, health policy researcher, and CEO of RevelAi Health. He is faculty at the Duke University School of Medicine and the Duke Margolis Institute for Health Policy.
References
Yelin E, Weinstein S, King T. The burden of musculoskeletal diseases in the United States. Semin Arthritis Rheum. 2016;46(3):259-260. BMUS Fourth Edition. https://www.bmus-ors.org/
Dieleman JL, Cao J, Chapin A, et al. US Health Care Spending by Payer and Health Condition, 1996-2016. JAMA. 2020;323(9):863-884. https://www.apta.org/news/2018/01/23/new-data-on-musculoskeletal-disease-highlight-its-position-as-major-contributor-to-health-care-costs
Safiri S, Kolahi AA, Cross M, et al. Prevalence, Deaths, and Disability-Adjusted Life Years Due to Musculoskeletal Disorders for 195 Countries and Territories 1990-2017. Arthritis Rheumatol. 2021;73(4):702-714. https://pmc.ncbi.nlm.nih.gov/articles/PMC10788788/
GBD 2021 Low Back Pain Collaborators. Global, regional, and national burden of low back pain, 1990-2020, its attributable risk factors, and projections to 2050: a systematic analysis of the Global Burden of Disease Study 2021. Lancet Rheumatol. 2023;5(6):e316-e329. https://pmc.ncbi.nlm.nih.gov/articles/PMC10234592/
Deyo RA, Mirza SK, Martin BI. Back pain prevalence and visit rates: estimates from U.S. national surveys, 2002. Spine. 2006;31(23):2724-2727. https://www.ncbi.nlm.nih.gov/books/NBK586768/
Centers for Disease Control and Prevention. Facts About Falls. Older Adult Fall Prevention. Updated 2024. https://www.cdc.gov/falls/data-research/facts-stats/index.html
National Council on Aging. Get the Facts on Falls Prevention. Updated 2024. https://www.ncoa.org/article/get-the-facts-on-falls-prevention/
Lewiecki EM, Ortendahl JD, Vanderpuye-Orgle J, et al. Healthcare Policy Changes in Osteoporosis Can Improve Outcomes and Reduce Costs in the United States. JBMR Plus. 2019;3(9):e10192. https://pmc.ncbi.nlm.nih.gov/articles/PMC6892455/
Williams SA, Daigle SG, Weiss R, Wang Y, Arora T, Curtis JR. Economic Burden of Osteoporosis-Related Fractures in the US Medicare Population. Ann Pharmacother. 2021;55(7):821-829. https://pubmed.ncbi.nlm.nih.gov/33750190/
Schett G, Gwin S, Engel A, et al. Musculoskeletal health: an ecological study assessing disease burden and research funding. Lancet Reg Health Eur. 2024;36:100783. https://pmc.ncbi.nlm.nih.gov/articles/PMC10788788/
Patel NK, Bozic KJ, et al. Medicare Reimbursement for Primary and Revision Total Hip and Knee Arthroplasty: An Updated Analysis From 2000 to 2024. J Arthroplasty. 2025. https://pubmed.ncbi.nlm.nih.gov/40262679/
Bedard NA, et al. Medicare Reimbursement for Primary Hip and Knee Arthroplasty Is Disproportionately Decreasing Relative to Other High-Volume Inpatient Procedures. J Arthroplasty. 2025. https://pubmed.ncbi.nlm.nih.gov/40349878/
Patel NK, Kerzner B, et al. The Trend of Medicare Reimbursement for Total Joint Arthroplasty: Using Mathematical Models to Predict Possible Per-Hour Rate Out to 2030. Arthroplasty Today. 2024;28:101415. https://pmc.ncbi.nlm.nih.gov/articles/PMC11295619/
Centers for Medicare & Medicaid Services. Calendar Year 2026 Medicare Physician Fee Schedule Final Rule (CMS-1832-F). https://www.cms.gov/newsroom/fact-sheets/calendar-year-cy-2026-medicare-physician-fee-schedule-final-rule-cms-1832-f
Shichman I, Roof M, Askew N, et al. Projections and Epidemiology of Primary Hip and Knee Arthroplasty in Medicare Patients to 2040-2060. JB JS Open Access. 2023;8(1):e22.00112. https://pmc.ncbi.nlm.nih.gov/articles/PMC9974080/
Trends in Medicare Arthroplasty Procedure Volume: Projecting From 2025 to 2040. J Arthroplasty. 2025. https://pubmed.ncbi.nlm.nih.gov/40505750/
American Association of Orthopaedic Surgeons. American Joint Replacement Registry Surpasses 4 Million Captured Procedures. 2024. https://www.aaos.org/aaos-home/newsroom/press-releases/american-joint-replacement-registry-surpasses-4-million-captured-hip-and-knee-arthroplasty-procedures/
Daigle ME, Weinstein AM, Katz JN, Losina E. The cost-effectiveness of total joint arthroplasty: a systematic review of published literature. Best Pract Res Clin Rheumatol. 2012;26(5):649-658. https://pmc.ncbi.nlm.nih.gov/articles/PMC3879923/
Centers for Medicare & Medicaid Services. Transforming Episode Accountability Model (TEAM). CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/team-model
BillingParadise. The CMS TEAM Model 2026: Survival Guide for Orthopedics. Published 2026. https://www.billingparadise.com/blog/cms-team-model-for-orthopedic-practices/
Electronic Code of Federal Regulations. 42 CFR Part 512 Subpart E, Transforming Episode Accountability Model (TEAM). https://www.ecfr.gov/current/title-42/chapter-IV/subchapter-H/part-512/subpart-E
Centers for Medicare & Medicaid Services. ACCESS Model. CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/access
Centers for Medicare & Medicaid Services. ACCESS Technical Frequently Asked Questions. https://www.cms.gov/priorities/innovation/access-technical-frequently-asked-questions
Longyear R. The CMS ACCESS Model Update and Payment Rates. Longyear Health (Substack). https://longyearhealth.substack.com/p/the-cms-access-model-update-and-payment
Benesch, Friedlander, Coplan & Aronoff LLP. CMS Announces New ACCESS Model. Published 2025. https://beneschlaw.com/resources/cms-announces-new-access-model-advancing-a-national-outcomes-based-framework-for-chronic-care-health-equity-and-community-integration.html
Prevounce Health. CMS Unveils the ACCESS Model: A New Era for Technology Enabled Chronic Care. Published 2025. https://blog.prevounce.com/cms-unveils-the-access-model-a-new-era-for-technology-enabled-chronic-care
Centers for Medicare & Medicaid Services. LEAD Model. CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/lead
ATI Advisory. CMS Announces the LEAD Model. Published 2026. https://atiadvisory.com/resources/cms-announces-the-lead-model/
Centers for Medicare & Medicaid Services. Long term Enhanced ACO Design (LEAD) Model Request for Applications. Appendix E: CARA Episode Specifications. Published March 2026. https://www.cms.gov/priorities/innovation/files/lead-rfa.pdf
Centers for Medicare & Medicaid Services. 2026 Medicare ACO Initiatives Participation Highlights. https://www.cms.gov/newsroom/fact-sheets/2026-medicare-accountable-care-organization-initiatives-participation-highlights
Fingerlakes1. ACO Success Strategies for Small and Rural Practices in the LEAD and MSSP Era. Published March 2026. https://www.fingerlakes1.com/2026/03/19/aco-success-strategies-for-small-and-rural-practices-in-the-lead-and-mssp-era/
RISE Health. Enhancing Risk Adjustment Programs with AI: What It Can and Can’t Do. Published 2026. https://www.risehealth.org/insights-articles/article/enhancing-risk-adjustment-programs-with-ai-what-it-can-and-cant-do/
Forvis Mazars US. What Physicians Should Know About CMS’ Ambulatory Specialty Model. Published January 2026. https://www.forvismazars.us/forsights/2026/01/what-physicians-should-know-about-cms-ambulatory-specialty-model
Centers for Medicare & Medicaid Services. 2026 Summary of Cost Measures. Published December 2025. https://www.cms.gov/files/document/2026-mips-summary-cost-measures.pdf
Centers for Medicare & Medicaid Services. ASM (Ambulatory Specialty Model). CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/asm
Centers for Medicare & Medicaid Services. WISeR Model. CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/wiser
Centers for Medicare & Medicaid Services. CMS Innovation Center Overview. https://www.cms.gov/priorities/innovation/overview
Centers for Medicare & Medicaid Services. MAHA ELEVATE Model. CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/maha-elevate
Centers for Medicare & Medicaid Services. CJR-X (Comprehensive Care for Joint Replacement Expanded) Model. CMS Innovation Center. https://www.cms.gov/priorities/innovation/innovation-models/cjr-x
Healthcare Financial Management Association. CMS FY27 Inpatient Rule: CJR-X Model and Payment Update. Published April 2026. https://www.hfma.org/payment-reimbursement-and-managed-care/cms-fy27-inpatient-rule-cjr-x-payment-update/
Centers for Medicare & Medicaid Services. CMS to Improve Patient Care Experience and Lower Costs for Hip, Knee, and Ankle Replacements. Press Release, April 10, 2026. https://www.cms.gov/newsroom/press-releases/cms-improve-patient-care-experience-lower-costs-hip-knee-ankle-replacements